TRANSMISSION // 2611.20322v1
When a maximum risk score can mislead an alert evaluation
Source published
A theoretical model shows how using the highest of repeated risk scores in a regression-discontinuity analysis can distort estimated effects when earlier alerts change later scores—even if the score density looks continuous.
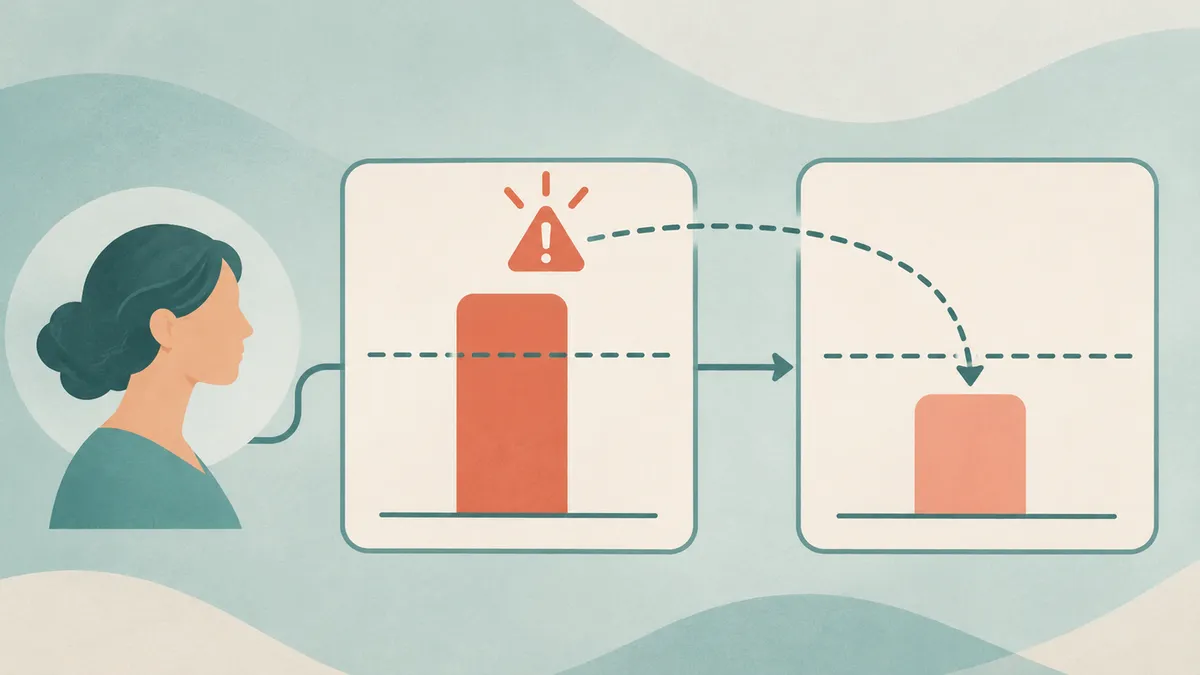
Hospitals may trigger alerts when a patient’s risk score crosses a threshold. But if an alert changes care, it may also change scores recorded afterward. A theoretical preprint examines what happens when researchers use the highest score during a stay to estimate an alert’s effect.
A patient’s risk score crosses a threshold, an alert is sent, and clinicians respond. Later scores may then reflect both the patient’s condition and the care prompted by the alert. That creates a challenge for researchers evaluating whether an alert helped: should they summarize the score history using its maximum, even when some scores came after treatment began?
In Maximum Scores and Treatment Feedback in Regression Discontinuity Designs, Subir Hait studies this question using a mathematical model of two assessments. The work focuses on regression discontinuity (RD), a method that estimates effects by comparing cases just above and below a treatment threshold. The central finding is that a maximum score can correctly classify whether a patient was ever alerted yet still produce an estimate that differs from the treatment’s causal effect.
How later scores can change the comparison
The model starts with an initial score and a later score that would be recorded without an earlier intervention. An alert at the first assessment can shift the second score. The patient is considered treated if either assessment triggers an alert, and the maximum of the observed scores identifies that treatment status correctly.
The difficulty is not misclassification. Rather, patients just above and just below the maximum-score threshold can differ in their underlying outlook because earlier treatment changed which later scores appear near the cutoff. The paper separates the RD contrast into the treatment effect and a “composition” term: a difference in the types of patients represented on either side of the threshold.
This result depends on assumptions, including a constant treatment effect across early and later treatment, no loss to follow-up, and regularity conditions around the cutoff. It is a theoretical analysis, not an evaluation of patient records from a hospital.
A continuous density is not always reassuring
When feedback shifts scores only in one direction, the paper shows that the composition term is linked to the relative jump in the density of the maximum at the cutoff and a contrast in patients’ underlying prognosis. In this model, an exactly continuous density then rules out bias. If there is a density jump, its size can help bound the bias—but translating that into a useful bound requires an assumption about how different the prognoses of affected patients can be.
When feedback can shift scores in both directions, movements may cancel in the density even while changing who appears near the threshold. In that case, a continuous density does not rule out bias. The paper develops bounds based on the total movement across the boundary, but these require additional assumptions about prognosis and score behavior. Its proposed confidence procedure for binary outcomes also relies on explicit sensitivity and smoothness assumptions; the author describes it as conservative and notes that it may produce wide intervals.
A model example illustrates the possibility, not a result from clinical data: with independent uniform scores, a true risk reduction of four percentage points appears as a one-point increase in the maximum-score RD contrast. Simulations also show that narrower bandwidths, robust bias correction, and flexible covariate adjustment do not remove this model’s composition bias. Those tools address other estimation problems; they do not, by themselves, restore the missing identification condition.
What researchers might do—and what remains uncertain
The paper presents an RD analysis using the initial, pre-intervention score as a benchmark. Under the model’s assumptions, a fuzzy RD—the ratio of the outcome change to the change in treatment probability—recovers the effect when early and late treatment have the same effect. This is not a universal fix: if treatment effects differ by timing, the analysis targets a more complicated question.
The model is deliberately limited. It has two assessments and excludes features such as irregular measurement, event-dependent censoring, and treatment effects that vary with timing. The paper does not establish that mixed-direction feedback occurs in any particular clinical alert system, and it explicitly does not reanalyze or assess any published clinical study. Its equations and simulations clarify a possible failure mode and the assumptions needed for bounds; they do not show how large that problem is in real hospitals.
The practical lesson is about study design: a score summary built from post-alert measurements may carry treatment feedback into the comparison itself. Researchers evaluating repeated-score alerts should explain why their chosen running variable supports a causal interpretation and, where possible, examine a pre-intervention score as well. This November 2026 arXiv version is a preprint; its claims should be read as theoretical results under stated assumptions, not as clinical evidence or established guidance.
- regression discontinuity
- causal inference
- clinical alerts
- risk scores
- treatment feedback
- preprint
Reviewed cross-references
These connections were reviewed by a model, not independently fact-checked by a human. Similarity does not imply agreement; consult the original papers and the evidence below.
How Medical Cutoffs Can Help Researchers Identify Treatment Effects
Shared method: Both papers discuss regression-discontinuity comparisons at a treatment threshold. Hait studies how using a maximum of repeated scores can alter the RD contrast when earlier alerts affect later scores; Cattaneo and Titiunik present the general RD framework and note that score timing or measurement can complicate causal interpretation. The latter is an introductory discussion, not an analysis of maximum-score feedback, so it does not independently validate Hait’s result.
Model review: · openai-codex/gpt-6-luna
Evidence and provenance
Selected excerpts, not complete papers. PDF extraction can omit figures or damage equations, tables and reading order; sources may be preprints.
2611.20322v1 — Original paper
Excerpt reference:
static/papers/2611.20322v1.md:55-95
Basis: Paper text
Source SHA-256:37f8d4bf02d3e61f4fdbb115016d7641f84fababb71a17b4dc82f8a864bc7d022508.03878v2 — Original paper
Excerpt reference:
static/papers/2508.03878v2.md:95-208
Basis: Paper text
Source SHA-256:15f7c9ae8142d6e52ff739ac879eda5aefa0b1f2f30df28696ed89c93a350d85
Related reading
Automatically matched by shared topic keywords. These links do not imply that the sources agree or establish a consensus.
How Medical Cutoffs Can Help Researchers Identify Treatment Effects
Source published
Shared keywords: causal inference, regression discontinuity
When grouping university majors changes what a causal estimate means
Source published
Shared keywords: causal inference, regression discontinuity
Better blood-pressure forecasts did not establish reliable surgical warnings
Source published
Shared keywords: clinical alerts
Estimating Long-Term Effects Across the Outcome Distribution
Source published
Shared keywords: causal inference
When Does Reviewing an AI Agent Actually Help?
Source published
Shared keywords: causal inference