TRANSMISSION // 2611.08649v1
VoluCompose compresses medical scans for AI while preserving benchmark performance
Source published
A preprint presents a training-free method that condenses the visual information passed to medical vision–language models. Across nine adaptive-budget tests, VoluCompose retained about 23% of visual tokens while exceeding uncompressed models on an aggregate benchmark measure—but the results do not establish clinical safety or equivalent real-world speed gains.
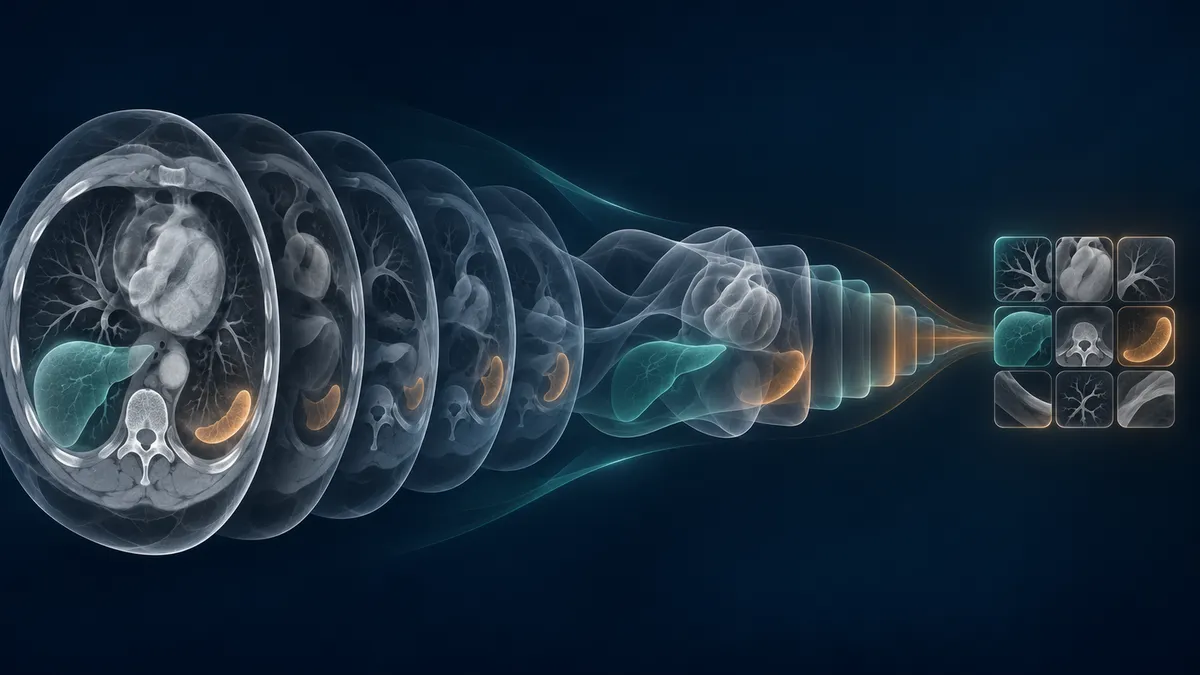
A three-dimensional medical scan can contain hundreds of closely related slices. VoluCompose tries to spare AI models from processing so much repeated information by separating two decisions: which visual features to preserve, and how much space to give them.
Why medical scans create an AI bottleneck
Vision–language models turn images into numerical representations called visual tokens, which a language decoder uses to generate answers or reports. A volumetric scan can produce a long sequence of these tokens because each slice contributes its own image patches. Processing that sequence increases computation and memory demand.
In the preprint VoluCompose: Constructing Compact Volumetric Visual Representations for Medical Image Understanding, Zanting Ye and colleagues propose compressing this information before it reaches the language decoder. The aim is not to compress the original scan file, but to build a shorter representation for an existing AI model.
Their starting observation is that neighboring slices repeatedly depict similar anatomy. Simply discarding tokens, however, risks losing localized differences such as lesions or anatomical boundaries.
Separating content from capacity
VoluCompose has two components. One constructs the compact representation; the other determines its token budget. Neither requires retraining the underlying model.
The content component groups consecutive slices with sufficiently similar features, retaining their order. Within each group, it averages features at corresponding image-grid positions. It then distributes the available tokens across groups, selects distinctive representative features called anchors, and blends each anchor with related features. This refinement adds context without increasing the selected token count.
To compare features, the method uses the Lorentz distance, a mathematical measure from hyperbolic geometry. Unlike cosine similarity, which compares feature directions, this measure incorporates both direction and magnitude. The authors argue that this helps distinguish information that simpler similarity rules can treat as equivalent. Feature magnitude is nevertheless a model-derived signal, not a direct measure of medical importance.
The capacity component examines attention in the visual encoder—the part of the model that processes images. It uses attention entropy to measure how spread out that attention is. Concentrated attention produces a smaller budget; dispersed attention produces a larger one. In the adaptive experiments, retention was capped at 30%. Compression uses neither the question nor the report text, allowing the same compact representation to serve multiple questions.
What the benchmark results show
The researchers tested question answering on M3D and 3D-RAD, and report generation on AMOS-MM. Four models were evaluated: Hulu-7B, MedGemma-1.5-4B, Qwen2.5-VL-7B and Qwen3-VL-8B.
Under a fixed nominal budget of 10% of visual tokens, VoluCompose achieved an average ROUGE-L score of 24.71, compared with 20.81 without compression. ROUGE-L measures overlap in word sequences with reference text; it is not diagnostic accuracy. Average closed-question accuracy was 57.22%, versus 55.73% without compression—a gain of 1.49 percentage points.
ROUGE-L exceeded the uncompressed result in 10 of the 12 dataset–model combinations. Its lowest ratio to the corresponding uncompressed score was 96.4%, compared with minima between 15.0% and 70.5% for the three fixed-budget competitors. These are worst-setting ratios, not guarantees for individual patients.
In nine adaptive-budget settings covering three models, VoluCompose retained 22.78% of visual tokens on average. Its mean relative quality was 121.68% of the uncompressed reference. That measure combines metric ratios using a geometric mean within each setting, then averages across settings. It does not mean 121.68% accuracy or a uniform improvement on every outcome.
VoluCompose also led the average combined quality-and-retention measure. However, competitor HiPrune scored better on that trade-off when results were averaged separately for Hulu-7B and Qwen3-VL-8B. VoluCompose’s largest advantage was on MedGemma.
Savings are estimated, not measured end to end
For the nominal 10% budget, the authors estimated reductions of 92.05% in decoder prefill computation and 89.23% in key–value cache demand. Prefill processes the input before generation; the cache stores information used during generation.
These estimates exclude image encoding and token composition. They therefore do not establish equivalent reductions in total running time, energy use or deployment cost.
Important limits remain
Compression did not improve every metric. On AMOS-MM with Hulu-7B at the 10% budget, ROUGE-L rose from 28.76 to 37.41, while METEOR, another text-matching measure, fell from 31.73 to 28.35. Component tests also found that a cosine-based variant outperformed the full method on MedGemma report metrics.
The evaluation relies on benchmark accuracy and text similarity, alongside selected illustrative cases. It does not establish prospective clinical safety or reliable preservation of rare findings. The main performance tables provide no confidence intervals, limiting assessment of uncertainty around differences.
This preprint supports a narrower conclusion: substantial token compression can preserve, and sometimes improve, measured performance on these tests. Whether those gains translate into dependable clinical assistance requires further validation.
- VoluCompose
- medical imaging
- vision–language models
- visual token compression
- volumetric scans
- hyperbolic geometry
- attention entropy
- AI efficiency
Related reading
Automatically matched by shared topic keywords. These links do not imply that the sources agree or establish a consensus.
Simple probes detect factuality signals inside quantized language models
Source published
Shared keywords: attention entropy
EvoML checks machine-learning workflows in stages and saves successful fixes
Source published
Shared keywords: medical imaging
Using generated ultrasound images to choose real ones worth labeling
Source published
Shared keywords: medical imaging
Mammography AI heat maps perform worse in dense breasts—but the reasons matter
Source published
Shared keywords: medical imaging
Why more AI tools alone may not deliver complete radiology reports
Source published
Shared keywords: medical imaging